
Immune changes after menopause are usually described as a decline. That word is doing too much work.
What the research describes is stranger and more specific: the immune system becomes more inflammatory and less effective at the same time. Both directions, simultaneously.
Why hormones reach immune cells at all
The connection isn’t indirect. T cells and B cells express oestrogen receptors — both ERα and ERβ[5], meaning oestrogen can modulate lymphocyte function directly.
Receptors are found across nearly all immune cell populations, including natural killer cells[1].
So when oestrogen declines, it isn’t that immune cells are affected by some downstream consequence. The signal they were receiving stops arriving.
What the review found
The foundational reference here is a Maturitas review that analysed 688 studies on immune function and menopause[2]. Its findings have been reproduced consistently since.
After menopause[3]:
- Increase in pro-inflammatory serum markers — IL-1, IL-6, TNF-α
- Increased responsiveness of immune blood cells to those cytokines
- Decrease in CD4 T lymphocytes and B lymphocytes
- Decrease in the cytotoxic activity of NK cells
Note the second item. Not only are there more inflammatory signals, the cells receiving them have become more responsive to those signals — which amplifies the effect rather than adding to it linearly.
The paradox
Put those four findings together and the shape becomes clear.
More inflammation. Fewer coordinating cells. Reduced killing capacity.
One description captures it well: the immune system becomes more inflammatory yet less effective — stronger signals with reduced precision[1].
This is the same two-directional problem we examined in the post on “boosting immunity.” Immune function isn’t a dial where higher is better, and post-menopausal change is a clear demonstration of why. The system here has moved in one direction on inflammation and the opposite direction on targeted response.
Anything described as raising immune activity would, in this context, be pushing on the side that’s already elevated.
Evidence it’s oestrogen, not only age
Menopause coincides with ageing, and ageing changes immunity on its own — a process termed immunosenescence[3]. Separating the two matters.
Two lines of evidence do that.
Surgical menopause. Women experiencing sudden oestrogen deficiency after oophorectomy showed increased IL-1, IL-6 and TNF-α[4]. The change appeared abruptly rather than gradually, which age alone wouldn’t produce.
Reversal with oestrogen. Those pro-inflammatory changes were reversed by oestrogen replacement therapy in multiple studies[4].
An intervention that reverses a change is strong evidence about what caused it.
Supporting data from a vaccination study: post-menopausal women receiving oestrogen therapy showed better preservation of naïve B cells, decreased CD4 T cell inflammatory cytokine production, and slightly lower circulating IL-6[5].
To be clear, none of this is a recommendation about hormone therapy. That decision involves many considerations beyond immune markers and belongs entirely with a clinician. What the data establishes is a causal direction, not a course of action.
Where IL-6 leads
One of those four findings has consequences well beyond infection.
IL-6 is a key factor in bone resorption, and is also associated with diseases more common after menopause — diabetes, atherosclerosis and cardiovascular disease[3].
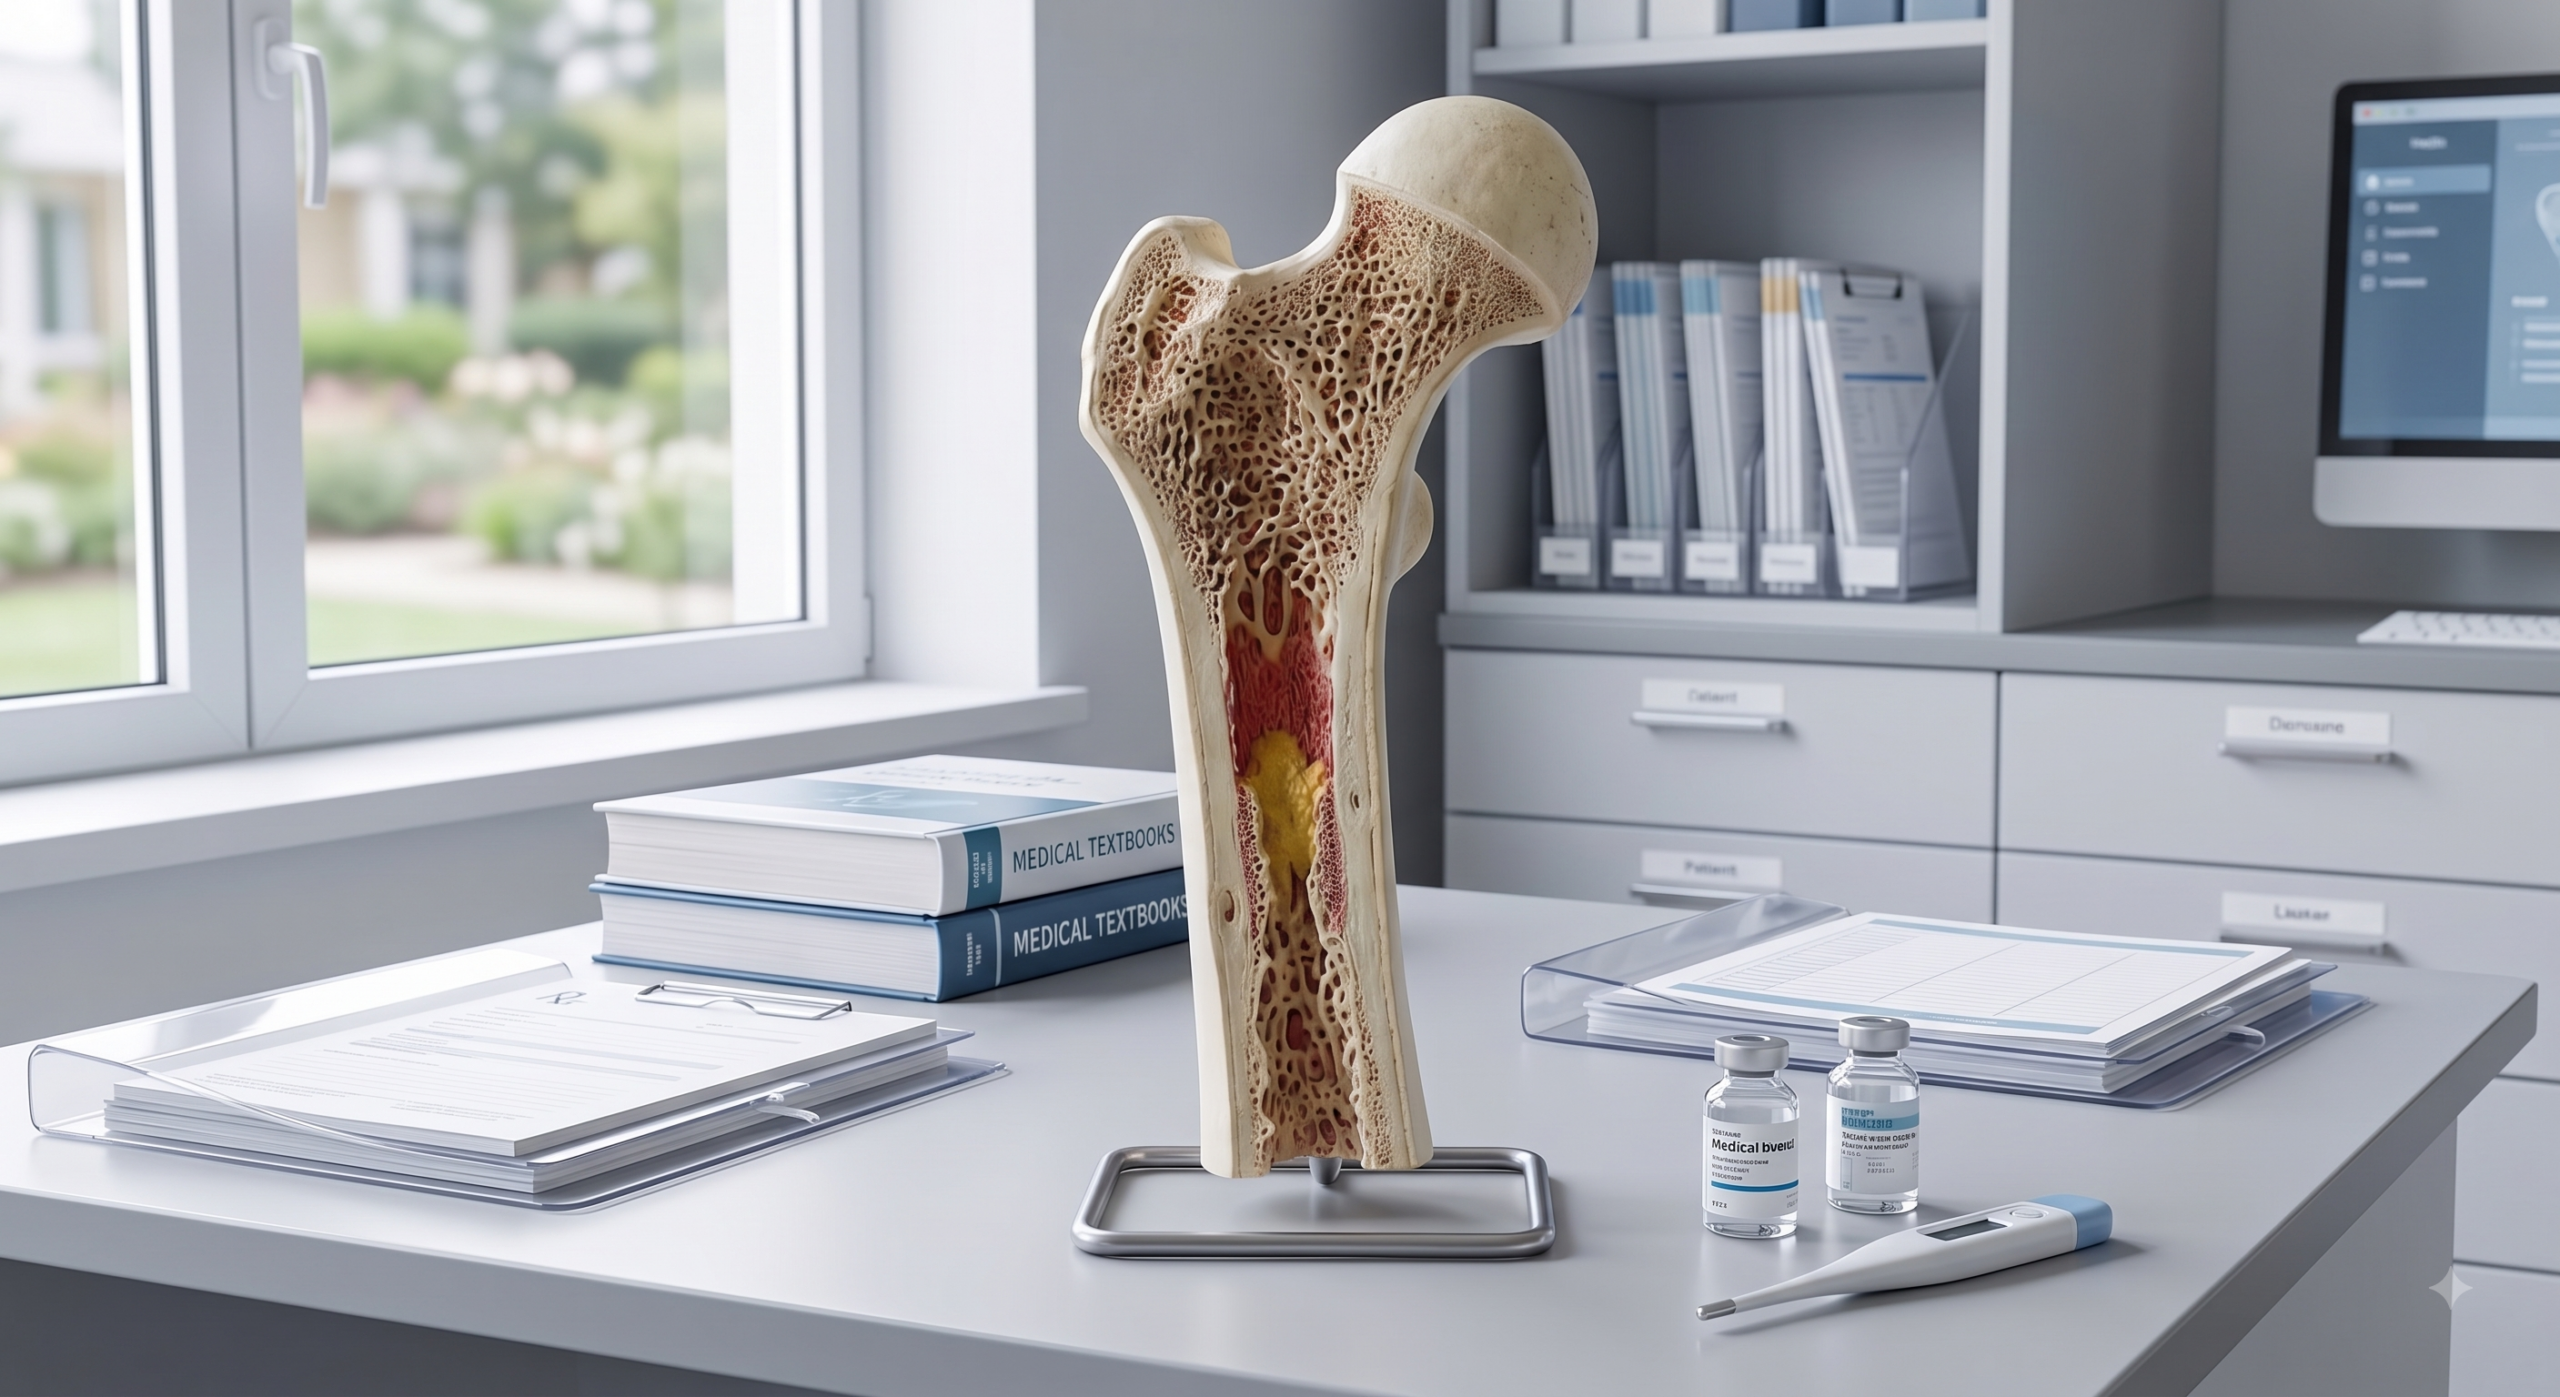
That’s a connection worth holding onto. The rise in bone loss after menopause is usually explained through oestrogen’s direct effects on bone. The inflammatory pathway is part of the same story: IL-6 activates osteoclasts, the cells that break bone down[6].
So the immune shift and the bone shift aren’t separate developments happening in parallel. They share a mechanism.
What follows practically
Given a shift in two directions at once, the useful responses are narrower than the marketing suggests.
Vaccination status is the one intervention that targets the weakened side specifically. Reduced NK activity and fewer CD4 cells mean less effective response to novel pathogens — which is precisely what vaccination trains in advance.
Existing autoimmune conditions may destabilise. Shifting immune regulation can unsettle conditions that were previously well managed[1]. If you have rheumatoid arthritis, lupus or Hashimoto’s thyroiditis, changes during this period are worth raising with your specialist rather than attributing to the condition alone.
Products framed as amplifying immune activity deserve scepticism here more than usual. The inflammatory side is already elevated.
Bone and cardiovascular monitoring becomes more relevant, given where IL-6 leads. The bone density and lipid posts in this series cover what those assessments involve.
Nutrient status is worth checking rather than assuming. A Korean review notes that vitamin D regulates both innate and adaptive immune responses, and that deficiency is linked to increased autoimmune activity and infection susceptibility[6]. That’s an argument for knowing your status, not for high-dose supplementation — a distinction covered in the vitamin D and falls post.
Closing
I expected this topic to be about immune decline, and the framing turned out to be wrong in an instructive way.
Decline suggests a single dimension moving down. What the 688-study review describes is inflammation rising and targeted response falling — the two failure directions we looked at in the immunity framing post, appearing together in one physiological transition.
That’s genuinely useful to know, because it makes most of the marketing in this space inapplicable. There is no setting to turn up. There’s a system that has moved off balance in two directions, and interventions worth considering are the ones that address the specific side that’s weakened.
At a Glance
- T and B cells express oestrogen receptors (ERα and ERβ) — the connection is direct
- A review of 688 studies found four consistent post-menopausal changes
- Pro-inflammatory markers rise — IL-1, IL-6, TNF-α — and cells become more responsive to them
- CD4 T cells and B lymphocytes decrease; NK cytotoxic activity decreases
- Net result: more inflammatory yet less effective — stronger signals, reduced precision
- Surgical menopause produced the same changes abruptly, and oestrogen therapy reversed them — evidence it’s oestrogen, not age alone
- IL-6 activates osteoclasts — the immune shift and post-menopausal bone loss share a mechanism
- Vitamin D regulates innate and adaptive immunity; deficiency is linked to autoimmune activity and infection susceptibility
※ This article describes physiological changes and is for general information only. It does not replace medical advice, diagnosis or treatment, and nothing here is a recommendation for or against hormone therapy — that decision involves considerations well beyond immune markers and belongs with your clinician. If you have an autoimmune condition, discuss any change in symptoms with your specialist. Do not begin high-dose supplementation on the basis of this information.
References
- “Menopause and Immune System: What Changes” (summary of the Gameiro review; autoimmune destabilisation), Samphire Neuroscience, https://www.samphireneuro.com/en-us/blog/menopause-and-immune-system
- “Menopause and the Immune System: What Changes and Why It Matters” (the inflammatory-yet-less-effective framing), Allergy Research Group, https://allergyresearchgroup.com/blogs/nutrition-in-focus/menopause-and-the-immune-system-what-changes-and-why-it-matters
- Gameiro CM, et al. “Menopause and aging: changes in the immune system — a review”, Maturitas 2010, https://pubmed.ncbi.nlm.nih.gov/20813470/
- “Menopause is an inflection point of age-related immune changes in women”, Journal of Reproductive Immunology (oophorectomy findings and reversal with oestrogen therapy), https://www.sciencedirect.com/science/article/abs/pii/S0165037821000760
- “Impact of Estrogen Therapy on Lymphocyte Homeostasis and the Response to Seasonal Influenza Vaccine in Post-Menopausal Women”, PMC, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4747494/
- “Vitamin D and the Immune System in Menopause: A Review”, Journal of Menopausal Medicine 2021, https://e-jmm.org/DOIx.php?id=10.6118%2Fjmm.21011